Address Common Barriers in Healthcare Improvement
Healthcare teams often have good reasons to hesitate before changing a process. Staff may face conflicting priorities, unreliable data, unclear decision authority, privacy requirements, or a risk that a small operational change could affect patient safety. A useful improvement plan identifies those conditions before the test and gives clinical, operational, and safety owners a clear role.
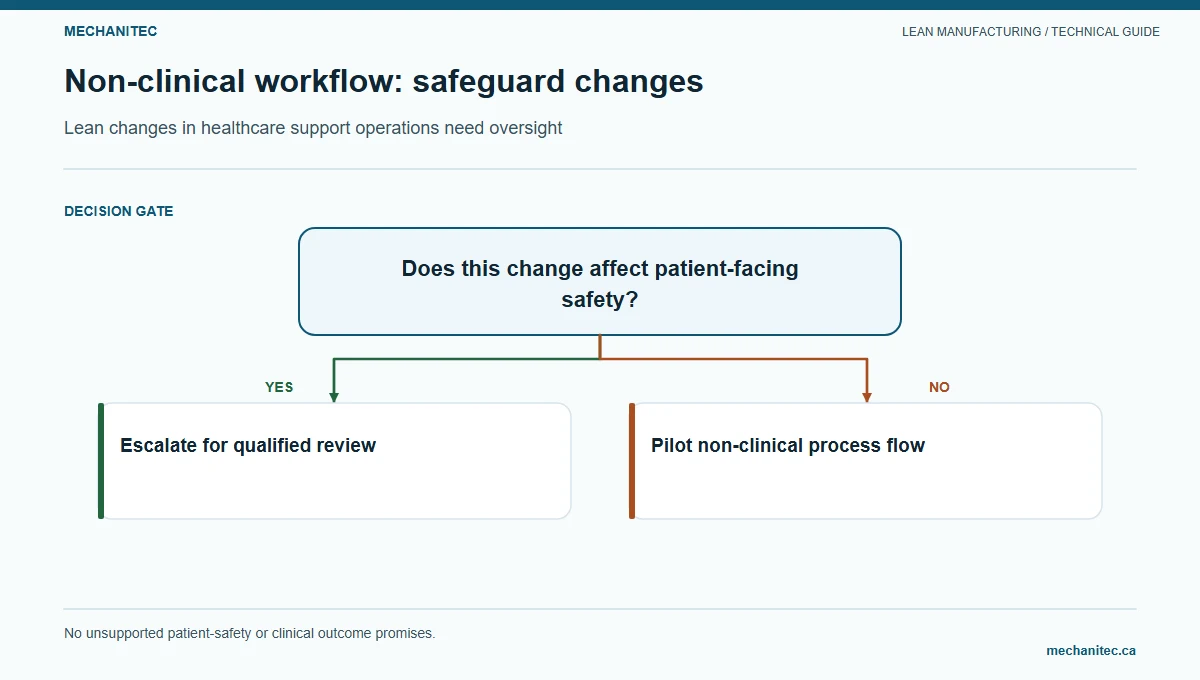
This article focuses on nonclinical workflow and support processes, such as replenishing facility supplies, routing equipment-service requests, coordinating schedules, and improving administrative handoffs. It does not provide clinical guidance or recommend changes to diagnosis, treatment, medication, infection control, or other patient-care procedures. Those changes require qualified clinical governance and the applicable institutional review.
Define the process and the boundary
Choose one nonclinical process with a clear start and finish. “Improve hospital efficiency” is too broad to test. “Reduce the time between a facilities equipment-service request and the first qualified response” is more specific. Name the location, request type, hours, included teams, and excluded work. If patient-care activity could be affected, state that clearly and stop until the appropriate clinical and risk owners define oversight.
Agree on what counts as the request, response, completion, and recurrence. A request submitted at the end of a shift may wait until the next staffed period; that is different from an unacknowledged request during staffed hours. Use dates and units consistently. Do not report a faster response by excluding nights, weekends, difficult cases, or requests that were not completed.
Map the handoff with people who use and support the process. Include frontline staff, facilities or operations, information technology if the record system is involved, privacy or compliance as needed, and the process owner. Ask what work is delayed, what information is missing, how urgent cases are distinguished, and which system is the authoritative record.
Identify barriers before a test
Several obstacles can look like “resistance” but need different responses:
- Unclear ownership: requests move between departments because no role owns triage, assignment, or closure. Map decision authority and assign a backup.
- Competing work: staff cannot participate because schedules do not protect time. Set a small test window and confirm coverage with the manager.
- Incomplete or inconsistent data: timestamps, locations, and categories are missing or defined differently. Audit a sample before calculating a baseline.
- Privacy or security concerns: the proposed tracker includes personal or sensitive details that are not needed. Minimize data and consult the responsible privacy and security functions.
- Safety or clinical impact: a support-process change could alter access, availability, environmental conditions, or care workflows. Involve qualified safety and clinical governance before a test.
- Staff distrust: previous suggestions received no response, or measures were used to rank individuals. Explain the purpose, protect appropriate confidentiality, and report decisions back.
- Unrealistic scope: the team tries to fix several departments at once. Narrow the boundary and list dependencies that need separate approval.
Separate an urgent risk from a gradual improvement opportunity. A hazard, suspected exposure, privacy event, equipment condition affecting safety, or process failure requiring immediate response must use institutional escalation channels. A Lean board or experiment log is not a substitute for those procedures.
Set governance and approval rules
Before testing a change, ask which people or committees must review it. The answer depends on the process, local policy, applicable regulation, and whether the change affects patient care, protected information, devices, facilities, or staffing. This article cannot determine those requirements for a particular organization.
Document a simple approval path. The process owner confirms the boundary and operating need. The clinical lead evaluates any potential care impact. Safety, infection prevention, facilities, privacy, security, quality, and compliance functions review changes within their scope. The manager verifies staffing and coverage. The person who controls the affected record or standard approves revisions. No pilot begins until the required owners say the proposed change is ready.
| Question | Owner to involve | Evidence or control | Pause when |
|---|---|---|---|
| Could this change affect a clinical task or patient access? | Clinical lead and designated governance body | Process map, affected roles, approved policy, clinical risk review | Impact or approval authority is unclear |
| Could it change a safety, facility, or environmental condition? | Safety, facilities, or EHS owner | Hazard review, site controls, emergency route, maintenance record | A required control is missing or degraded |
| Does the data contain sensitive or identifiable information? | Privacy, security, and records owner | Minimum necessary fields, access rules, retention and approved system | The proposed tool is not authorized for the data |
| Who can change the standard or system? | Document, application, or process owner | Current revision, change request, training and rollback plan | Team cannot restore the approved method |
| Can staff test the change without unsafe workload? | Department manager and affected staff | Coverage plan, training time, shift-by-shift participation | The trial depends on unapproved overtime or missed duties |
Use small tests with reliable measures
The Institute for Healthcare Improvement’s Model for Improvement asks teams to define what they aim to accomplish, how they will know a change is an improvement, and what change they can test. Its Plan-Do-Study-Act cycle is designed for learning from a small test in the real setting. In healthcare, a small test still requires the organization’s safety, clinical, privacy, and governance rules. “Small” does not mean “unreviewed.”
Use one primary measure and guardrails. For a facilities request process, the primary measure could be elapsed hours from a complete request to acknowledgement during staffed hours. Guardrails might include urgent-request response, repeat calls, request completeness, workload, and safety events. Define how to handle requests that are missing required information and distinguish acknowledgement from resolution.
Collect a baseline using existing authorized records. If fields are missing, first improve the recording method or report the uncertainty. Do not create a second spreadsheet of personal data without approval. Use aggregated or de-identified information when that meets the purpose and local rules.
When comparing periods, account for operating hours, staffing, request type, and planned closures. Report the count and denominator beside a rate. If requests are grouped by urgency, preserve those categories; a faster average can conceal a slower response to the highest-risk group. Document missing records and excluded cases so that reviewers can reproduce the calculation.
A useful test record includes the question, planned change, who approved it, where and when it will run, the main measure, guardrails, stop conditions, and the date for review. Assign one person to capture deviations. If staff adapt the change to keep work moving, record the adaptation; otherwise the team may evaluate a version of the process that was never actually used.
For operational processes, include balancing measures. A new supply route might reduce trips for one unit while increasing delivery burden for central stores. A revised appointment or service-request queue might shorten average waits while leaving a subgroup with longer waits. The team should check for this shift before recommending wider use.
Illustrative example: equipment-service request handoff
Illustrative example — not observed healthcare performance. A hospital’s nonclinical equipment-service requests sometimes move between facilities and department teams without a clear owner. Staff report that the status is difficult to find. The operations manager proposes a single intake route for a limited category of room-maintenance requests.
Before any change, the manager checks whether the category can affect patient care, emergency response, infection prevention, security, or environmental controls. The relevant owners confirm that urgent or clinical equipment requests stay in their existing approved channels. Privacy and information security review what data the intake form can collect and where it can be stored. Staff who submit and fulfill requests identify the minimum fields needed to route work.
The team defines an eligible request, acknowledgement, assignment, completion, and urgent escalation. It reviews a small sample of historical records to see whether timestamps are reliable. If they are not, the team fixes the data definition and collection method before using a baseline. The test runs for one department and one request type, with a named operations owner and daily review of any misrouted request.
Measures include time to acknowledgement, time to assignment, requests returned for missing information, misroutes, repeat contacts, and any safety or clinical escalation. The change stops if an urgent request is diverted from the existing channel or if unapproved information enters the new tracker. At the review, the team decides whether to adjust the form, change routing rules, or end the trial. It does not claim patient outcome improvement from a support-process measure.
Listen to staff and close the loop
Staff participation depends on the quality of response. Explain what the team can decide locally and what needs more review. Acknowledge reports with a next step and date. If an idea is deferred, explain the constraint and tell the person when it will be reconsidered. If the suggestion is outside scope, route it to the correct channel rather than closing it without direction.
Use brief check-ins to ask whether the process is easier to use, whether any role has extra work, and whether the change creates a new workaround. Avoid comparing employees by individual cycle time or number of ideas. Measures should help the team learn about the process, not penalize staff for reporting problems.
Review open actions at a cadence that fits the risk. Urgent safety and clinical issues follow immediate procedures. Routine nonclinical requests can use a weekly operational review. A monthly governance check can examine repeated delays, data quality, access, privacy, and whether a successful test became a controlled standard.
Plan a responsible first month
- Week 1: select a nonclinical process, define its boundary, identify users and risks, and confirm approval owners.
- Week 2: audit authorized records and observation methods; refine the measure and data fields.
- Week 3: design a small reversible change, document guardrails and stop conditions, and obtain required approval.
- Week 4: run the limited test, review staff feedback and measures, and decide whether to adjust, stop, or request a broader review.
The dates are planning prompts; governance review or data correction may take longer. Do not set a launch deadline that encourages staff to bypass approval. Use the IHI Model for Improvement for the aims, measures, and test cycle, and keep clinical decisions within qualified institutional governance. For a related manufacturing application of controlled replenishment, see the nonclinical facilities-supply restocking guide.
First-review checklist
- Does the process stay within a clearly stated nonclinical boundary?
- Have clinical and safety owners reviewed any possible effects on patient care or risk?
- Does the trial use only approved information systems and minimum necessary data?
- Can staff stop or escalate the test without delay?
- Are measures defined with units, timestamps, and exclusions?
- Is workload covered on every affected shift?
- Does the plan include a rollback and a feedback route for staff?
- Will the team avoid claims about patient outcomes unless those outcomes were properly measured and reviewed?
Start by recording one process measure from an approved data source and one staff-reported barrier. Keep the records separate until the team confirms they describe the same process condition. That gives the group a basis for a safe, specific test.





