Lean Restocking for Nonclinical Hospital Supplies
A hospital facilities team can lose time when a maintenance technician reaches a work area and finds that a routine supply is missing from the service cart. The issue may be unclear ownership, uneven restocking, a part stored in the wrong place, or an order signal that arrives after the stock is gone. You can study this workflow without changing patient care: choose a small group of nonclinical supplies, record when each restock signal appears, and test a controlled replenishment routine with the facilities and supply-chain owners.
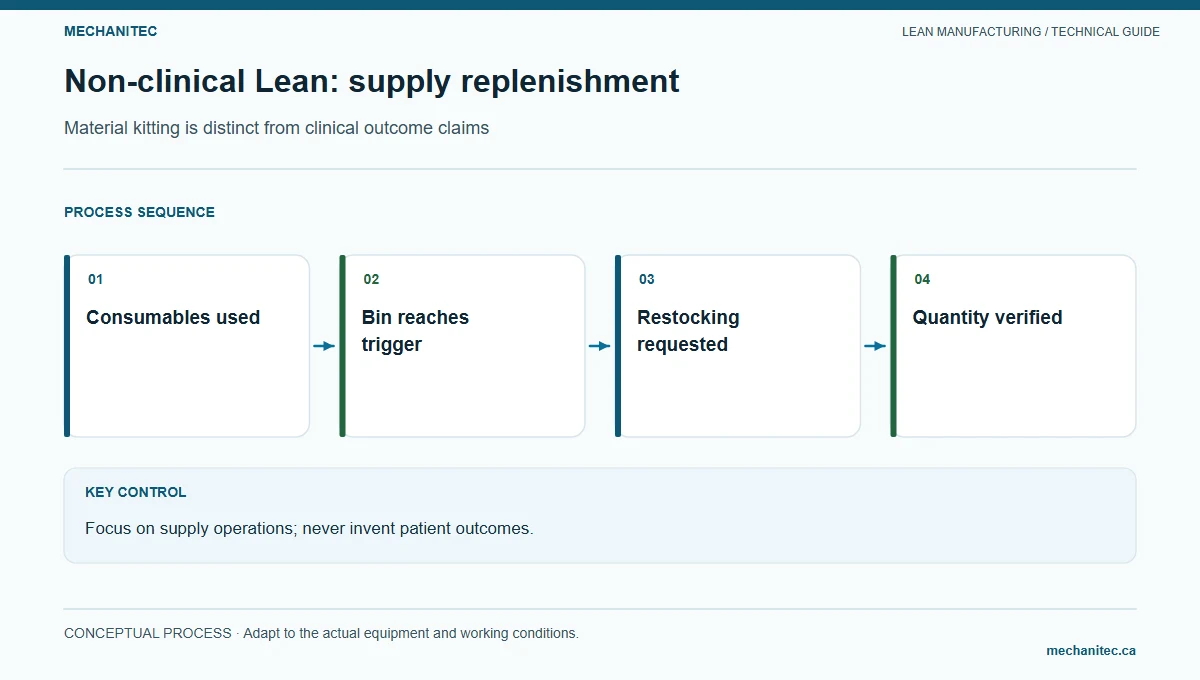
This guide is limited to nonclinical supplies used by facilities or administrative support teams. It does not give patient-care advice or instructions for medications, sterile processing, surgical instruments, clinical devices, personal protective equipment, or other controlled clinical inventory. Keep those items under the hospital’s approved clinical, regulatory, and infection-prevention procedures. Do not alter custody, cleaning, sterilization, inspection, storage, release, or traceability rules.
Choose a safe, bounded restocking problem
Start with a facilities-maintenance service cart or a nonclinical supply point that has a clear owner. Select a few repeat-use items such as label rolls, cable ties, or a specified fastener kit. Confirm with the site’s safety, infection-prevention, facilities, and supply-chain owners that the chosen items and storage location are appropriate. Exclude chemicals, clinical consumables, safety-critical equipment, and any item with controlled storage or special handling unless the responsible department explicitly defines the approved process.
Set a clear boundary: the measure begins when an authorized worker signals that an approved item needs replenishment and ends when the cart is ready for the next facilities work order. This is a restocking measure. It does not represent a patient waiting time, equipment uptime, clinical response, or safety outcome.
Record an item’s identifier, approved description, unit of measure, location, stock condition, reorder source, replenishment lead time, and owner. If two items look similar but are not interchangeable, keep their labels and storage positions distinct. Use approved procurement sources; do not substitute an item based only on appearance or availability.
Map the material and information handoff
A simple current-state map should show both the physical item and the signal that tells someone to replace it. Lean Enterprise Institute describes a supermarket as a location with predetermined standard inventory where a downstream user withdraws what is needed and that withdrawal sends a replenishment signal upstream. A small hospital supply point may use that principle, but the local owner must set item eligibility, quantity, location, and approvals.
| Step | Facilities or supply-team action | Information to record | Handoff check |
|---|---|---|---|
| Use or withdrawal | Worker takes an approved item for a facilities work order | Item ID, quantity, time, and service-cart location | Does the label match the approved item and unit? |
| Restock signal | Worker moves a card, scans a bin, or records a low-stock signal | Signal time, on-hand quantity, reorder point, and owner | Can the signal be seen by the person responsible for replenishment? |
| Request and approval | Supply owner checks approved source and order route | Order quantity, source, approval, and expected delivery | Is the request within purchasing and stock limits? |
| Receive and verify | Authorized worker checks item, quantity, condition, and location | Receipt time, discrepancy, lot or expiry detail if required by policy | Does the item meet the site’s receiving and storage procedure? |
| Cart replenishment | Worker replenishes the approved position and updates stock | Restock time, quantity, and next review time | Is the cart ready, labeled, and in its approved location? |
Observe the process before drawing a better version. Follow a few real restock events across the people who withdraw, order, receive, and replenish the supplies. Check whether a signal gets lost in email, whether a requisition needs approval, whether an item is received but left in a staging area, or whether the cart is restocked only after a request arrives. Record approved workarounds as exceptions instead of presenting them as the standard process.
Use one definition for “ready.” For example, a facilities service cart is ready when every selected item is present at its labeled position, within its approved storage condition, and available for the next assigned facilities work order. The definition should not imply the technician is authorized to repair clinical equipment; the work order and qualification rules still control the task.
Calculate an initial replenishment point
Illustrative example — fictional facilities supplies, not observed hospital data: assume a facilities team uses four label rolls per workday. The approved supplier lead time is estimated at three workdays, and the team agrees to hold one additional workday of safety stock while it checks the variation in demand and delivery. The simple reorder point is:
Reorder point = average daily use × replenishment lead time + safety stock
4 rolls/day × 3 days + 4 rolls = 16 rolls.
If each labeled bin holds eight rolls, the signal should trigger replenishment when the inventory position reaches two bins, or 16 rolls. Inventory position means usable on-hand stock plus confirmed orders not yet received, minus any allocations already committed. The facilities and purchasing owners must define the local record and calculation before using it. This example does not set a recommended stock level.
| Item | Assumed use | Assumed lead time | Assumed safety stock | Calculated reorder point | Illustrative bin size |
|---|---|---|---|---|---|
| Label rolls | 4 rolls per workday | 3 workdays | 4 rolls (1 workday) | 4 × 3 + 4 = 16 rolls | 8 rolls; signal at 2 bins |
| Cable ties | 20 ties per workday | 2 workdays | 20 ties (1 workday) | 20 × 2 + 20 = 60 ties | 30 ties; signal at 2 bins |
| Fastener kits | 2 kits per workday | 4 workdays | 4 kits (2 workdays) | 2 × 4 + 4 = 12 kits | 6 kits; signal at 2 bins |
These values exist only to show the formula. Actual usage can vary by season, work-order mix, scheduled maintenance, supplier reliability, or a change to an approved part. A replenishment point cannot replace a manufacturer’s service interval, purchasing rules, environmental controls, or required stock policy. If a part has a maintenance interval or expiration rule, keep that control in the system that owns it.
Keep a wait-time log for nonclinical equipment kits
For each facilities work order that needs a prepared tool-and-supply kit, record when the request arrives, when the kit is picked, when a missing item is identified, when the item is replenished, and when the kit is ready. Keep the work-order category general and omit patient names, room details, or clinical information. If a kit includes calibrated tools or safety equipment, follow the site’s qualification, inspection, and calibration rules; the log does not authorize their use.
| Kit request | Request received | Pick started | Missing item found | Item replenished | Kit ready | Wait from request to ready | Exception note |
|---|---|---|---|---|---|---|---|
| F-01 | 08:00 | 08:05 | None | Not needed | 08:18 | 18 min | Routine pick |
| F-02 | 08:15 | 08:20 | 08:22 | 08:55 | 09:00 | 45 min | Label rolls below bin quantity |
| F-03 | 09:10 | 09:12 | None | Not needed | 09:20 | 10 min | Routine pick |
| F-04 | 10:00 | 10:04 | 10:08 | 11:00 | 11:05 | 65 min | Fastener kit missing; order status checked |
| F-05 | 13:00 | 13:05 | 13:08 | 13:20 | 13:25 | 25 min | Restock tote at approved storage point |
For this fictional five-event sample, the wait times are 18, 45, 10, 65, and 25 minutes. Sorted, they are 10, 18, 25, 45, and 65 minutes; the median is 25 minutes. Their mean is 32.6 minutes: (18 + 45 + 10 + 65 + 25) ÷ 5. The mean and median describe only these invented events. In a real review, show the number of events, dates, item group, and any excluded requests so a reader can interpret the result.
Separate elapsed wait from hands-on picking time. A long elapsed wait with a short replenishment task may indicate a handoff or visibility problem. A long pick time may indicate that the layout, label, kit list, or location is unclear. Record both only if the team can collect them consistently. Do not turn a small sample into a claim about the entire hospital.
Set a safe replenishment routine
Write a short standard for the chosen nonclinical cart. It can state the item description, labeled location, approved quantity, signal method, responsible role, receiving check, restock cadence, and escalation path. Lean Enterprise Institute’s standardized-work reference describes a documented work sequence and standard inventory as elements for consistent process execution. In this setting, use the concept to make an approved routine visible and improvable; do not let a local Lean standard override hospital policy.
Choose a review cadence that fits use and procurement. A facilities owner might inspect the selected bins at the start of each workday and replenish from an approved supply point, while a purchasing owner reviews open orders and exceptions on a set schedule. These are planning options, not universal hospital procedures. The actual cadence should reflect consumption, supplier lead time, storage, staffing, and the responsible department’s rules.
During review, check the signal time, inventory position, confirmed order, expected receipt, missing quantity, and next owner. When a bin is empty, use the approved exception route, record the cause, and tell the requesting team what to expect. Do not borrow stock from another department, substitute a component, or remove a controlled item from its normal location without authorization.
Test one change on a small scale
The Institute for Healthcare Improvement describes Plan-Do-Study-Act as a method for documenting and learning from a small test of change. For a facilities supply routine, a test might make one labeled restock signal easier to see or move a nonclinical fastener bin to an approved point nearer the team’s work area. Ask the local facilities and supply-chain owners to approve the change before it starts. If the item or location could affect infection prevention, fire protection, building compliance, clinical service, or patient access, include the responsible safety or clinical authority.
- Plan: name the nonclinical item group, location, owner, start date, measure, and safety checks.
- Do: try the signal or restock routine for a small number of work orders.
- Study: review time from signal to restock, kit wait, stockouts, duplicate orders, and staff feedback.
- Act: keep, change, or stop the test based on the evidence and approvals.
Use an outcome measure such as the share of selected kits ready when the facilities work begins, a process measure such as signal-to-restock time, and balancing measures such as excess stock, duplicate purchasing, misplaced inventory, and time spent counting. These are operational measures for the selected support process, not patient-care outcomes.
Know when the method does not fit
A simple two-bin signal may be a poor fit when demand is highly irregular, an item is expensive, stock expires, the supplier is unreliable, or the item is subject to controlled access. An empty-bin signal also cannot protect against a long supplier interruption unless the owner plans an approved contingency. In those cases, retain the required procurement or risk controls and investigate a better service arrangement with the department responsible for the item.
Stop the test if the new layout hides labels, creates an unsafe storage condition, increases trip or handling risk, exposes restricted inventory, or encourages a substitute that has not been approved. Restore the prior approved arrangement and notify the responsible owner. For any sterile, clinical, medication, or patient-care item, leave the restocking and custody process under the appropriate clinical procedure.
Do not describe this workflow as a way to reduce patient harm, improve treatment, or improve clinical outcomes. This article makes no such claim. It gives a bounded method to study selected nonclinical facilities supplies and equipment-service kits.
Start with one facilities cart
- Ask facilities, supply chain, and safety owners to approve a nonclinical item group and location.
- Record the item, unit, current quantity, usage, supplier lead time, and reorder owner.
- Agree on the signal, the restock definition, and the exception process.
- Log request, pick, missing-item, replenishment, and ready times for a small sample of work orders.
- Separate elapsed waiting from hands-on work and count stockouts and duplicate orders.
- Test one approved change and review its operational and safety checks.
- Document the result and its sample size before making a broader claim.
For constraints on Lean improvement in healthcare organizations, see the healthcare improvement safeguards guide. For a manufacturing example of current- and future-state mapping, see the value-stream mapping guide.
Sources
- Lean Enterprise Institute: Supermarket — defines a predetermined inventory location and replenishment signal.
- Lean Enterprise Institute: Pull Production — describes downstream need signaling to upstream supply.
- Lean Enterprise Institute: Standardized Work — describes documenting a work sequence and standard inventory.
- Institute for Healthcare Improvement: Testing Changes with PDSA Cycles — supports learning from small, documented tests in local settings.